









Deadline tracking

Recert deadlines, tracked automatically
The system flags the window before it closes, so nothing slips past a deadline.
Baba is human-led, AI-enabled. We add an engagement layer between a health plan and its members. Advocates call, find the provider, arrange the ride, and stay on the task until it is closed.

Noelle from Baba
A trained expert that builds member trust and closes quality gaps
Member saves a single contact in their phone or downloads our app
This level of trust lets us intervene early and close gaps (especially gaps that require engagement over time).
More accurate data sent back:

We support your complex and hard-to-reach members
Advocates work on the practical problems that sit between a care plan and a completed visit.
The advocate gets the follow-up on the calendar, sends the discharge summary to the PCP, and checks the medication list while there is still time to prevent a return trip.

Ninety-day fills, pharmacy sync, mail order, and the prior-authorization call that still needs to be made. Adherence is logistics before it is behavior.
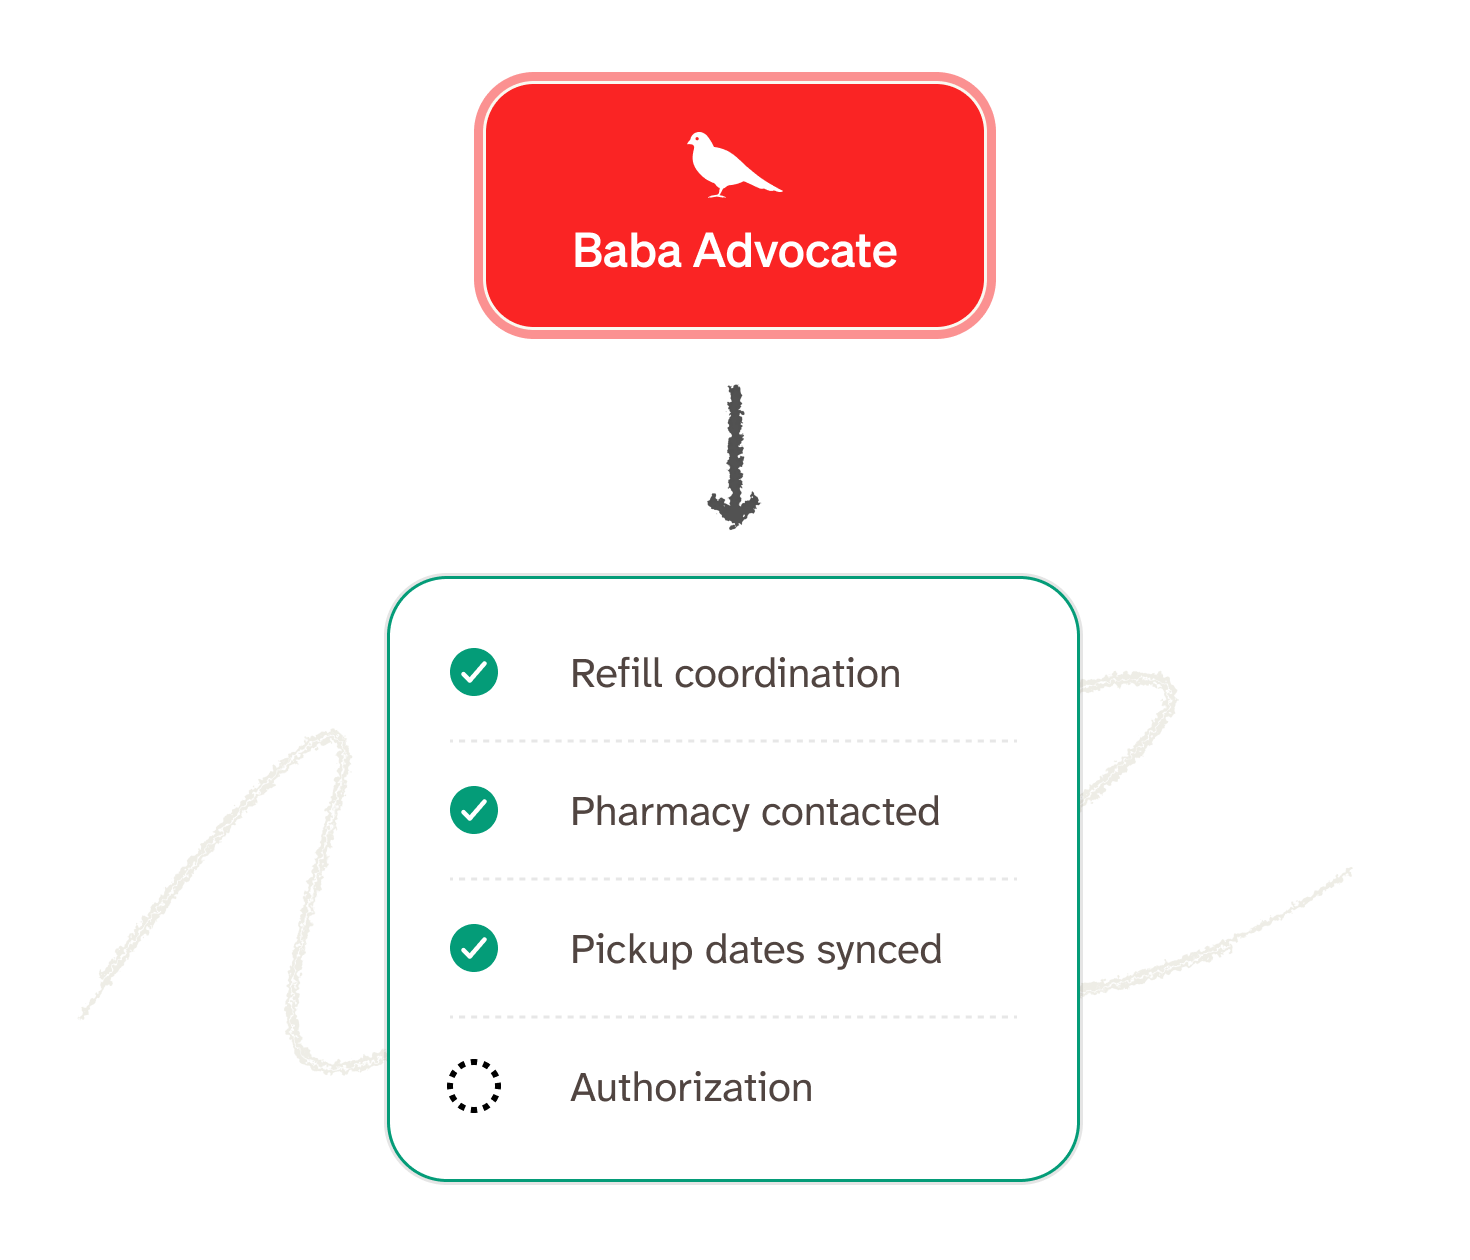
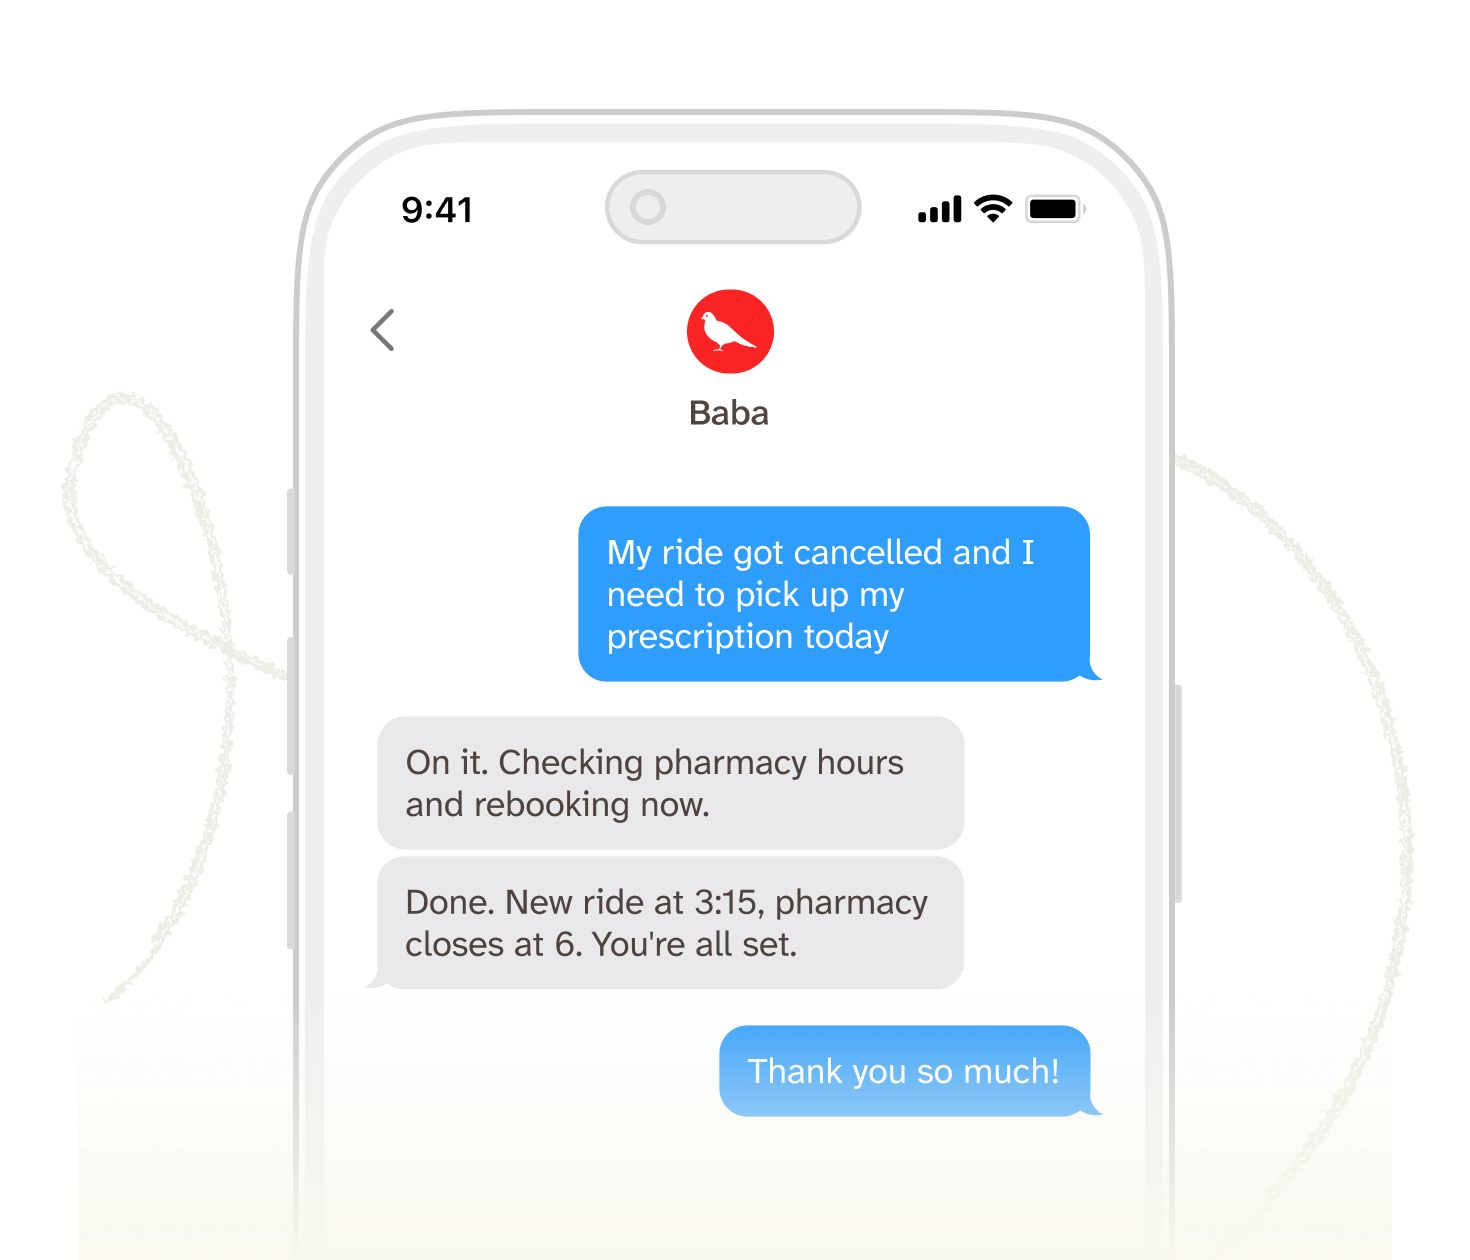
When transport falls through or a benefit is unclear, an advocate fixes the immediate problem before the emergency room becomes the fallback.

From studies with Baba-style community health workers, chronic care management programs, transition coaching, and patient navigation.

returned per $1 invested in community health worker support, among high-need patients
Health Affairs, 2020
lower Medicare spending per member per month in CMS’s evaluation of chronic care management
CMS evaluation, 2017
fewer 30-day readmissions among older adults who received transition coaching
Archives of Internal Medicine, 2006
breast and colorectal screening completion with patient navigation, across 30+ trials
J. General Internal Medicine, 2020Medicaid enrollment (and recertification) and Medicare Advantage HRAs are confusing processes with important deadlines. An advocate tracks dates, gathers documents, and files before things lapse.
The system flags the window before it closes, so nothing slips past a deadline.

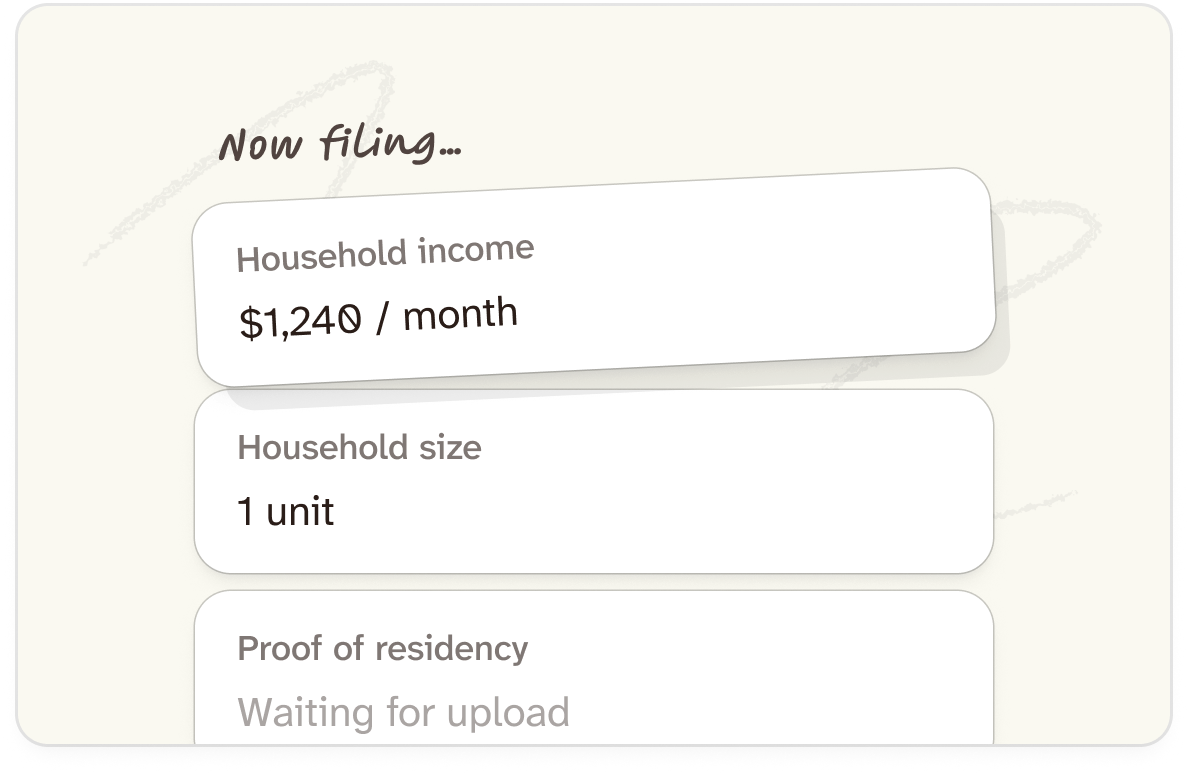
Documents gathered, forms completed, application submitted — not a task for the member.

No cold screening. The advocate already has what's needed to check eligibility.

CAHPS is double-weighted. Members answer “getting needed care” from lived experience: whether someone helped them get the appointment, refill, or ride.
JAMA Internal Medicine, 2018
Tell us what you are evaluating. We will follow up to schedule a conversation.